 Phoebe Wilson
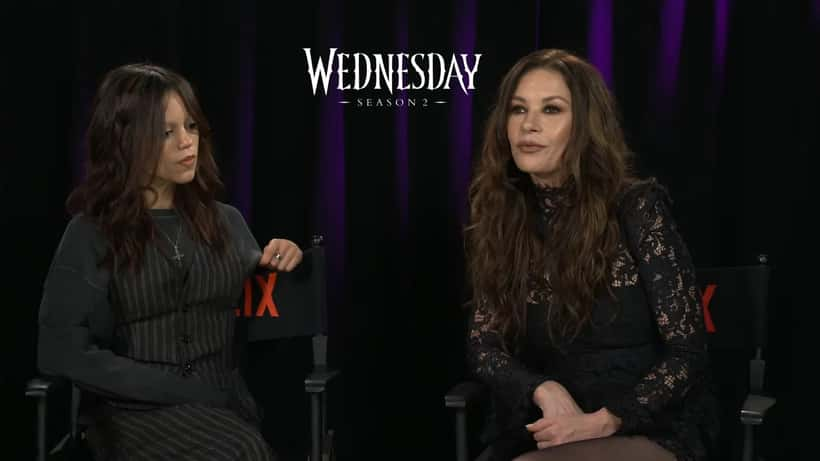
When Catherine Zeta-Jones returns to screens as Morticia Addams in Wednesday Season 2 — which premiered on Netflix on 6 August 2026 — millions of UK viewers are watching more than one of Hollywood's great performers. They are watching a woman who, in 2011, became one of the first major celebrities to speak publicly about living with bipolar II disorder: a diagnosis that still carries significant stigma across Britain. With her public profile higher than it has been in a decade, her story is prompting a genuinely useful question for the one in fifty adults in England who share the same condition — when does a shift in mood, energy, or behaviour cross the threshold that warrants professional help?
Wednesday Season 2 and the Renewed Spotlight on Zeta-Jones
The Netflix series brought Catherine Zeta-Jones back into the conversation in a significant way. Season 2 expanded Morticia Addams' role considerably, leaning into the maternal and psychological complexity of the character — a choice that resonated with audiences and critics alike. But it was a parallel story, away from Nevermore Academy, that caught wider attention.
In November 2025, a TikTok interview promoting the new season went viral for the wrong reasons: online commentary fixated on her appearance rather than her performance. Her response — posted on Instagram on 12 December 2025 — was characteristically composed: "Grateful for the role, ignore the noise — age is a privilege." Mental health professionals note that this kind of measured response, the ability to acknowledge an attack without being destabilised by it, is itself a marker of well-managed mood disorder. It is not a sign that the condition has disappeared. It is a sign of sustained, professional-supported work.
Bipolar II affects approximately 2% of UK adults — an estimated 1.4 million people in England alone, according to NHS England data. The vast majority of them are not celebrities with the resources to access swift, high-quality care. Many wait years before receiving a correct diagnosis.
What Bipolar II Disorder Actually Involves
Unlike bipolar I, which includes at least one full manic episode, bipolar II is defined by hypomanic episodes — elevated or irritable mood lasting at least four days — alternating with depressive episodes that can persist for weeks or months. This asymmetry matters. The hypomanic phase often feels productive, even exhilarating: less sleep but more energy, faster thinking, greater confidence. The problem arrives when that phase ends.
According to NICE (National Institute for Health and Care Excellence) guidelines, approximately 40% of people with bipolar II disorder wait more than ten years between the onset of symptoms and receiving a correct diagnosis. The most common misdiagnosis is unipolar depression — particularly in women — because hypomanic episodes are frequently interpreted as positive personality traits rather than clinical signals. A person told by colleagues they are "on fire this week" may not recognise that they have barely slept in three days.
A GP or health consultant with specialist knowledge in mood disorders looks for something specific: a cyclical pattern over time, not a single difficult week. The clinical picture requires at least two distinct episodes — one hypomanic, one depressive — to even begin an assessment conversation. Many people arrive at a professional consultation with years of undocumented cycles they have attributed to stress, diet, or seasons.
The Warning Signs That Prompt Professionals to Act
Health experts identify five patterns that consistently appear in referrals for bipolar spectrum assessment in the UK:
Sustained elevated periods lasting four or more days in which the person sleeps noticeably less than usual without feeling tired, speaks faster, and initiates significantly more projects or social engagements than normal.
Cyclical low periods lasting two or more weeks — not just a bad few days — in which motivation, concentration, and self-worth are measurably reduced.
Impulsive decision-making during elevated phases: financial commitments, relationship changes, or professional risks that the person later regards as out of character.
Significant disruption to work or relationships — not mild inconvenience, but measurable lost productivity, missed commitments, or strained partnerships that recur across multiple cycles.
A family history of mood disorders. Bipolar disorder carries a heritability of approximately 60 to 80%, according to research published in Nature Genetics. Having a first-degree relative with a bipolar diagnosis increases a person's lifetime risk substantially — a factor that should always be disclosed to a GP or consultant.
None of these patterns in isolation is definitive. Their combination, repeated across time, is what drives a clinical referral.
When the Numbers Make It Clear: A Realistic Scenario
Consider a 38-year-old woman in Leeds who has described to herself as having "high-energy phases" for the past four years. During these phases, she sleeps around four hours a night for days at a stretch, launches two or three new projects simultaneously, spends on average £500 to £700 more in a single week than she does normally, and feels a persistent sense that everything is accelerating in a good direction. Then, without warning, she enters a period lasting three to four weeks in which she struggles to get out of bed before noon, withdraws from friends, and cannot sustain concentration for more than twenty minutes.
If this pattern has repeated two or more times within a twelve-month period, NICE guidelines classify it as a potential bipolar spectrum condition requiring clinical assessment — not a personality type, not burnout, not overwork.
If the elevated phases last at least four consecutive days AND the low phases last at least fourteen days AND both are causing measurable disruption — lost workdays, financial strain, relationship tension — then a GP referral to a psychiatrist is clinically indicated. The challenge, in England, is timing: current NHS waiting times for a first psychiatric assessment average eighteen weeks. For someone in an acute depressive phase, eighteen weeks is not an abstract bureaucratic delay. It is a significant gap in care.
This is precisely why private mental health consultations have grown substantially in uptake. A private consultation with an experienced health consultant can typically be arranged within days rather than months. It does not replace NHS care — it compresses the timeline for receiving an initial assessment, a provisional framework, and a pathway forward. For a person who has spent years telling themselves their cycles are normal, that compression can be genuinely consequential.
For a helpful overview of how bipolar disorder is diagnosed and managed in England, the NHS bipolar disorder guide offers a reliable starting point before any clinical appointment.
What to Do If You Recognise Yourself in This Story
The most useful first step is structured observation, not immediate action. Keep a daily mood log for four to eight weeks. Each morning, note your energy level (1–10), hours slept, and any significant decisions or withdrawals from your usual routine. Note the date of any period that feels notably elevated or depressed. After eight weeks, read it back.
If you identify two or more cycles that match the pattern above — elevated periods of four or more days followed by low periods of fourteen or more days, with measurable disruption in both — book a GP appointment and specifically request a mood disorder assessment. Bring your log. GPs in England respond significantly better to documented patterns than to retrospective verbal accounts.
If NHS waiting times are a barrier, a private health consultation is worth considering. On Expert Zoom, you can connect directly with a health consultant experienced in mood disorder assessment — available within days, not months. The goal is not to receive a diagnosis from a single conversation; it is to have a properly informed professional review your documented pattern and tell you whether onward referral is warranted.
Catherine Zeta-Jones has spoken about the relief that comes from finally understanding what is happening. "Once I was diagnosed," she told one interviewer, "I was no longer fighting an invisible enemy." For the estimated 1.4 million people in England living with bipolar II — many of them undiagnosed — that description of relief is not a celebrity anecdote. It is a realistic outcome of getting the right professional input at the right moment.
You do not need to wait for the cycle to become unmistakeable. You need to start tracking it — and then ask for help from someone who knows what to look for.
This article is for informational purposes only and does not constitute medical advice. If you are concerned about your mental health, please consult a qualified health professional or contact your GP.
Related reading: Catherine Tate at Red Nose Day 2026: What Comedian Burnout Teaches Us About Creative Professional Wellbeing
